NEVERQUIT 60 KICKBOXING
LIABILITY WAIVER & RELEASE
1. Acknowledgment of Program Nature
I, _________________________________ (Participant), understand that NEVERQUIT 60 Kickboxing is a high-intensity, non-contact fitness and neuro-physical training program that may include boxing-based drills, heavy bag or mitt work, aerobic exercise movements, paced walking, balance and gait exercises, stretching, resistance training, core strengthening, getting up and down from the floor, and other adaptive or seated activities. I acknowledge that I have been advised to consult with a physician, to obtain medical clearance appropriate for my condition and level of activity, and to provide a Physician’s Clearance form to NEVERQUIT 60 prior to participation.
If I provide a physician’s release or clearance form that includes limitations, conditions, or restrictions on my participation, I agree to communicate those limitations to NEVERQUIT 60 staff and to participate only within the scope of the clearance I have received. I understand that NEVERQUIT 60 staff are not medical professionals and are not responsible for monitoring or enforcing any physician-imposed limitations. I accept full responsibility for ensuring that my participation remains within any restrictions set by my physician, and I release the Releasees from any claims arising from my exceeding or departing from those limitations or from any claim that NEVERQUIT 60 failed to enforce, monitor, or accommodate such limitations.
2. Assumption of Risk
I am aware that participation in boxing-based fitness involves inherent risks, including those arising from strenuous exertion, rapid or repetitive movement, balance and coordination challenges, use of equipment, contact with bags, mitts, floors, or other surfaces, acts or omissions of other participants, and my own physical condition, diagnosis, medications, or undisclosed limitations. These risks include, but are not limited to:
· Falls and Balance: Risks associated with rapid movement, pivoting, gait exercises, transfers, floor work, and changes in direction or elevation, which may be heightened by my underlying neuro-muscular condition, mobility limitations, or fatigue.
· Cardiovascular Stress: Risks associated with high-intensity interval training (HIIT), aerobic exertion, elevated heart rate, shortness of breath, dizziness, fainting, blood pressure changes, or other cardiovascular events.
· Physical Injury: Including muscle strains, sprains, joint injuries, bruises, fractures, aggravation of pre-existing conditions, dehydration, exhaustion, illness, exposure to infectious disease, or other serious injury. I voluntarily assume all risks, known and unknown, associated with my presence at, travel to or from, and participation in the program.
3. Rules, Conduct, and Participant Responsibility
I agree to follow all instructions, safety rules, and participation guidelines provided by NEVERQUIT 60 Kickboxing staff, to use equipment and facilities only as directed, and to stop activity and notify staff immediately if I feel pain, dizziness, shortness of breath, or any other sign of distress.
4. Waiver and Release of Liability
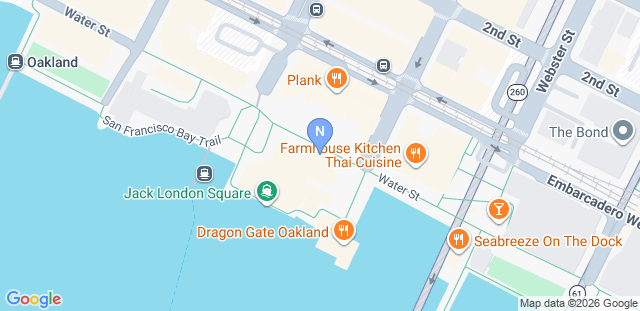
In consideration of being permitted to participate, I hereby release, waive, and forever discharge NEVERQUIT BRAND, LLC d/b/a NEVERQUIT 60 Kickboxing, its owners, members, managers, employees, contractors, trainers, instructors, volunteers, agents, representatives, affiliates, successors and assigns, the Port of Oakland, and the owners and occupants of any premises used for the program (collectively, the “Releasees”), from any and all claims, demands, causes of action, damages, losses, liabilities, costs, or expenses for personal injury, illness, death, or property damage arising out of or relating to my presence at the facility, use of the premises at 419 Water Street, participation in the program, or use of any equipment, to the fullest extent permitted by law, including claims based on the ordinary negligence of any Releasee. I further agree not to sue any Releasee on any such claim.
I understand that this release extends to claims that I do not know or suspect to exist in my favor at the time of signing. I expressly waive the protections of California Civil Code § 1542, which provides: “A GENERAL RELEASE DOES NOT EXTEND TO CLAIMS THAT THE CREDITOR OR RELEASING PARTY DOES NOT KNOW OR SUSPECT TO EXIST IN HIS OR HER FAVOR AT THE TIME OF EXECUTING THE RELEASE AND THAT, IF KNOWN BY HIM OR HER, WOULD HAVE MATERIALLY AFFECTED HIS OR HER SETTLEMENT WITH THE DEBTOR OR RELEASED PARTY.”
5. Not a Medical Provider
I understand that NEVERQUIT 60 Kickboxing instructors are fitness professionals and not medical doctors, neurologists, or licensed physical therapists. The services provided do not constitute medical advice, diagnosis, or medical treatment, and NEVERQUIT 60 does not undertake to monitor my health condition. I remain solely responsible for obtaining medical advice and treatment as needed.
6. Emergency Medical Authorization
In the event of an emergency, illness, injury, or other condition that staff reasonably believe requires prompt attention, I authorize the staff of NEVERQUIT 60 to contact 911, obtain emergency medical assistance, contact my emergency contact listed below, and share relevant health or contact information as reasonably necessary for emergency response. I understand that NEVERQUIT 60 is not obligated to provide such assistance and that I accept financial responsibility for any medical evaluation, transport, treatment, or related expense.
7. COVID-19 & Infectious Disease
I acknowledge the contagious nature of COVID-19 and other illnesses and voluntarily assume the risk of exposure by attending an indoor facility. I agree not to attend classes or enter the facility if I am experiencing symptoms of contagious illness, have been advised to isolate, or would otherwise create an unreasonable health risk to others.
8. Miscellaneous
This waiver shall be governed by and construed in accordance with the laws of the State of California, without regard to conflict of laws principles. If any provision of this waiver is held to be invalid or unenforceable, the remaining provisions shall remain in full force and effect. In any action arising out of or relating to this waiver, the prevailing party shall be entitled to recover its reasonable attorney fees and costs to the extent permitted by law.
9. Signature Acknowledgment
I have carefully read this Liability Waiver & Release, understand its contents, understand that I am giving up substantial legal rights, and sign it voluntarily and without reliance on any statement not contained in this form. I understand that this agreement is intended to be binding on me and, to the extent permitted by law, on my spouse, heirs, family members, estate, representatives, and assigns.
Emergency Contact
Name: _________________ Phone: ______________ Email: ___________
Participant Printed Name: ________________________________________________________
Participant Signature: ____________________________ Date: ____________________
[ ] Approved [ ] Probationary (4-Week Trial) [ ] Waitlisted (For New Class)
NEVERQUIT BRAND, LLC
419 Water Street * Oakland, CA 94607 * (510) 421-3328
 NEVERQUIT Brand LLC